

Benedict’s Law – Findings and Implications for Schools and EYFS Providers
Five-year-old Benedict Blythe died on 1 December 2021 after an allergic reaction at his primary school in Stamford, Lincolnshire. Almost five years later, the changes his family campaigned for are law.
From September 2026, every local-authority-maintained school, academy and pupil referral unit in England must have a published allergy safety policy, and must have regard to new statutory guidance on allergy safety. Further duties covering staff training, spare adrenaline devices and incident recording are coming through Regulations.
This article explains what happened to Benedict, what the inquest found, what Benedict’s Law actually requires, and what schools, nurseries and colleges should be doing now. It also covers the parts that are commonly misreported, including who is and is not covered, and what allergy awareness training means as distinct from first aid training.
Who Benedict was
Benedict Blythe was a bright, much-loved five-year-old from Stamford. He had multiple severe allergies — cow’s milk, eggs, peanuts, sesame and chickpeas — as well as asthma. He had experienced anaphylaxis before, including a serious reaction at nursery when he was two, after being given cow’s milk on his Weetabix.
On the morning of 1 December 2021 he went to school as usual, with allergy arrangements in place. He had been slightly unwell a couple of days earlier and had been kept off the previous day, but he was well that morning. He brought a biscuit from home, and had oat milk in his own cup at school.
During morning break, after his snack and milk, Benedict vomited. Staff believed he might have a sickness bug and telephoned his parents to collect him. He vomited again, and when he was taken outside for fresh air, he collapsed.
What the inquest found
The inquest concluded that the school did not follow all of the measures that were in place to prevent a fatal reaction. The jury identified risks of contamination with other milk, and delays in administering adrenaline
. The coroner issued a Prevention of Future Deaths report.The lessons that matter most for every school and early years setting:
- Vomiting can be an early sign of anaphylaxis. In a child with known severe allergies, sudden vomiting should always raise the possibility of a reaction.
- Delay in giving adrenaline is the single most dangerous factor. Delays in administration are consistently associated with fatal outcomes.
- Never move a child who may be having a reaction. Help and medication must come to the child, not the other way round. Walking a child to the office, or taking them outside, is dangerous.
- Allergy plans must be followed consistently, including during busy periods and when usual staff are not there.
- All staff need training, not just designated first aiders — a reaction can happen in the playground, the dining hall or a corridor.
- Earlier allergic incidents must trigger a procedural review. A near miss that is not learned from is a warning that has been wasted.
- Communication between staff is critical, particularly at handover and at break times.
Benedict’s parents, Helen and Peter Blythe, established the Benedict Blythe Foundation and campaigned with clinicians, allergy charities and policymakers for consistent national protections. That campaign became known as Benedict’s Law.
What Benedict’s Law actually is
Benedict’s Law is not a standalone Act of Parliament. It is the name given to a set of national protections now delivered through two things working together:
1. Section 34 of the Children’s Wellbeing and Schools Act 2026, which amends section 100 of the Children and Families Act 2014. It requires maintained schools, academies and PRUs to have allergy safety policies, publish them and keep them under review, and to have regard to statutory guidance on allergy safety. It also allows the Secretary of State to make further allergy safety requirements through Regulations, including requiring schools to stock spare adrenaline devices and to provide allergy safety training.
2. The DfE’s statutory guidance, Allergy safety in schools, published on 6 July 2026, which sets out how schools should meet that duty. It comes with an allergy safety policy template and an Individual Healthcare Plan template.
The guidance sits alongside the existing statutory guidance, Supporting pupils at school with medical conditions.
What is in force now, and what is still to come
This distinction is widely blurred in the coverage, and it is worth being precise about.
- Statutory duties from September 2026:
- Have an allergy safety policy, publish it, and keep it under review
- Have regard to the Allergy safety in schools guidance
- Stated Government intentions, to be introduced through forthcoming Regulations:
- A duty to stock spare adrenaline auto injectors
- A duty to ensure all staff receive regular allergy awareness training
- A duty to record serious incidents and near misses

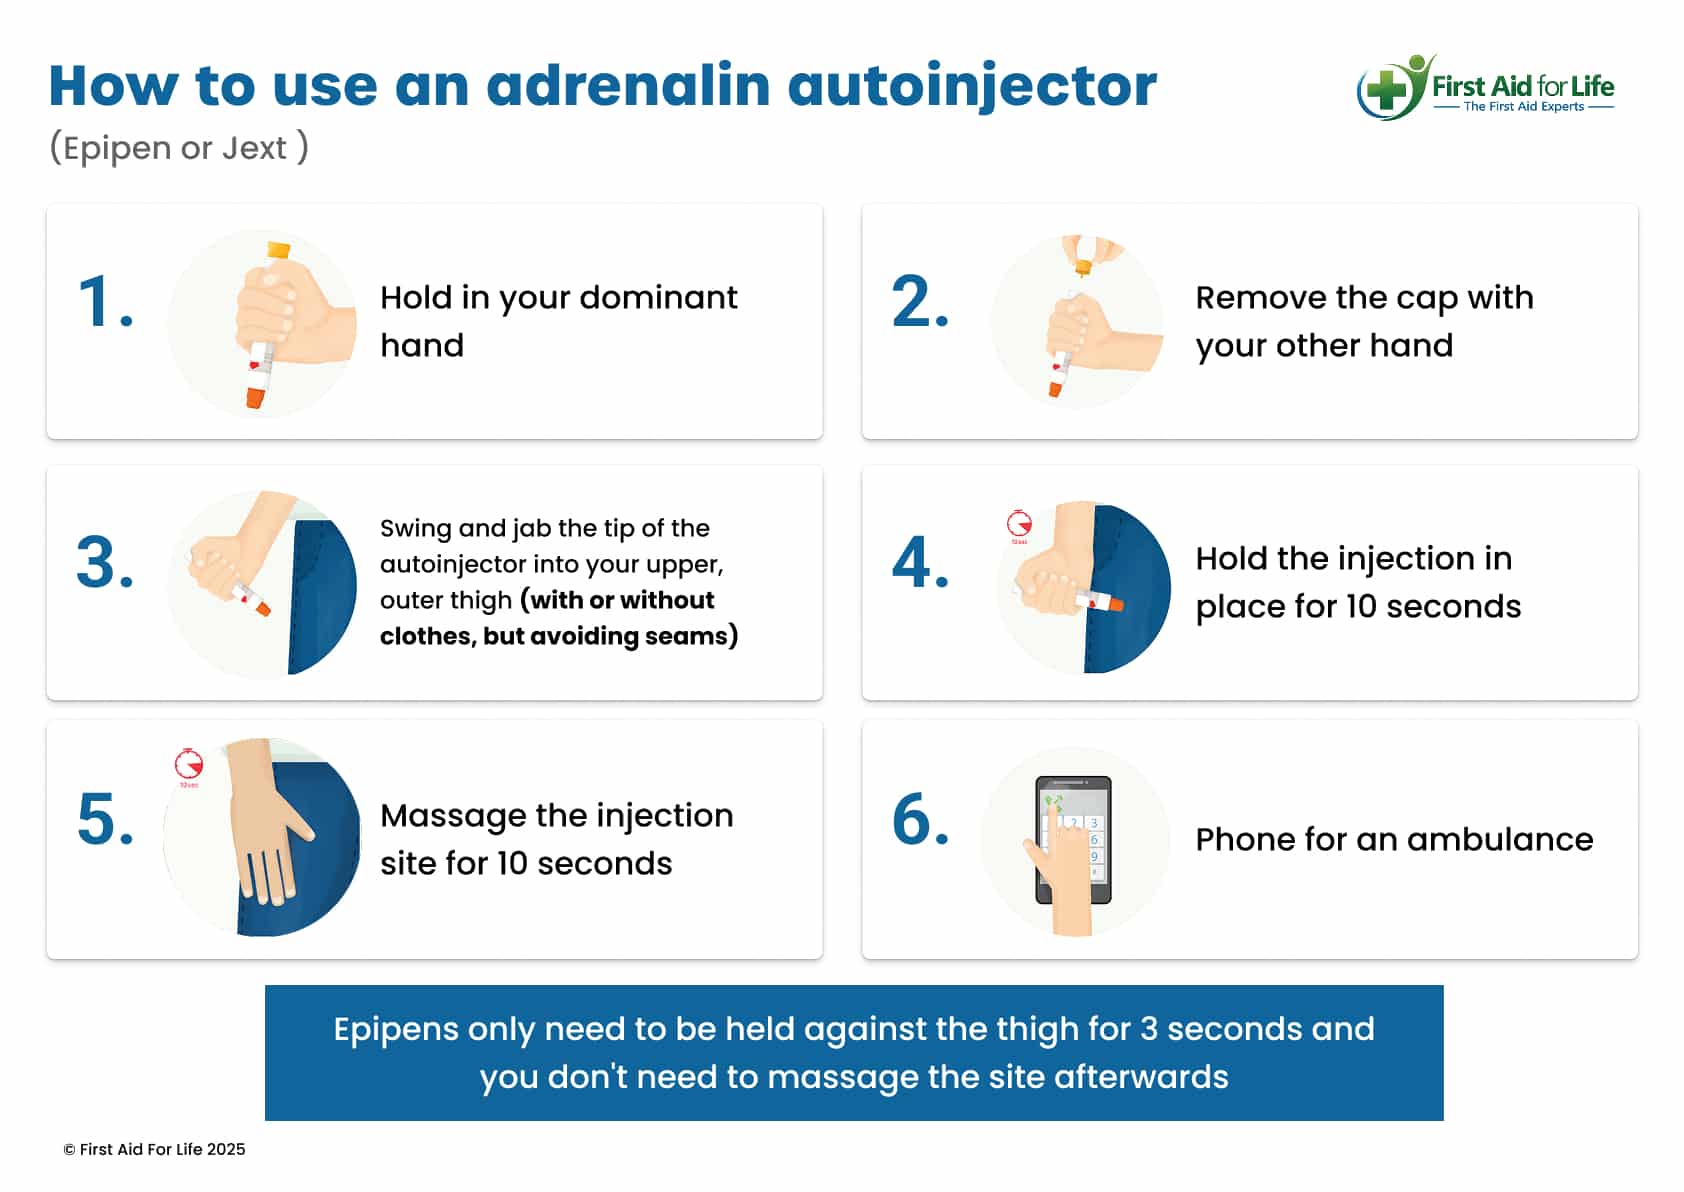
To download the poster for free click on the image above.
Who is covered, and who is not:
Must comply with the guidance:
- Governing bodies of maintained schools, including special schools
- Management committees of pupil referral units
- Proprietors of academies, including free schools and alternative provision academies, but not 16–19 academies
Not yet covered, but will be: independent schools, including independent special schools, and non-maintained special schools. The Government intends to introduce equivalent requirements through the Independent School Standards and the Non-Maintained Special Schools Regulations.
Good practice only: early years settings, FE colleges and other post-16 institutions. The guidance is explicit that it will be of relevance to these settings and should be treated as good practice.
The spare adrenaline point that catches early years settings out
The Human Medicines (Amendment) Regulations 2017 permit schools in England to buy spare adrenaline auto-injectors from a pharmacy without a prescription. Those Regulations apply to schools only. Early years settings and FE colleges are not permitted to stock spare devices in this way.
If you run a private, voluntary or independent nursery on a school site, you can ask the school whether its spare devices could be accessed in an emergency. If you are a standalone setting, you cannot currently hold spares at all, which makes it doubly important that every child at risk of anaphylaxis has both of their own prescribed devices with them, and that every member of staff can recognise a reaction and act.
The six core actions for schools
The guidance expects a school’s arrangements to cover:
1. A dedicated allergy safety policy, separate from the medical conditions policy, published on the website, reviewed at least annually, with a named member of the senior leadership team responsible for it. The guidance is direct that this responsibility should not be left with a catering manager. Allergy risk should sit on the school’s risk register.
2. Whole-school allergy awareness training, at least annually.
3. Individual Healthcare Plans for any child whose allergy requires supportive arrangements, developed with the child and their parents and taking account of clinical advice.
4. Access to prescribed adrenaline devices at all times, including travelling to and from school, at lunch, in the playground, on the sports field and on trips.
5. Spare adrenaline devices stocked, stored and managed properly.
6. Recording and learning from serious incidents and near misses.
Allergy awareness training: why first aid training is not enough
“Schools must have regard to this statutory guidance in fulfilling their duty to produce an allergy safety policy.” It states that standard first aid training is not sufficient and schools must undertake separate allergy awareness training.
First aid training teaches you to recognise and treat an emergency. Specific allergy awareness training does that too, but it also covers prevention, the school’s own systems, record-keeping, wellbeing and reporting. A first aider knows how to use an auto-injector. Allergy awareness training makes sure the lunchtime supervisor knows which children are on the allergy record, where the spare devices live, and what to do about the near miss last Tuesday.
Who must be trained: all staff present at times when pupils are scheduled to be on site. The guidance names permanent staff, temporary staff, supply teachers, peripatetic staff, agency workers and regular volunteers. It includes catering staff and anyone overseeing children at breakfast or after-school clubs. It does not extend to contractors with no pupil-facing role, such as builders or electricians.
How often: regularly, and at least annually. The policy should also set out induction arrangements for new staff and how supply and cover staff are covered.
DfE requires 14 specific training outcomes to be covered on the allergy awareness course:
The guidance sets out twelve bulleted outcomes, the seventh of which has three sub-points, making fourteen discrete checkpoints in all. Training should ensure that all staff:
- Have an awareness of allergy, the risks it poses, how allergic reactions can occur and how to manage it.
- Understand that allergy includes multiple conditions, food allergy, asthma, eczema, hay fever and others, which can co-exist.
- Understand the difference between food allergy, coeliac disease and food intolerance.
- Know where to find information on allergy triggers.
- Can identify the range of symptoms of allergic reactions.
- Understand and can recognise anaphylaxis.
- Know how to respond in an emergency, including: – calling emergency services and informing parents. – how to locate and administer emergency medication: adrenaline for anaphylaxis, an asthma reliever inhaler for an asthma attack. – training on how to use the medication or device in an emergency, whether prescribed to a named
- person or one of the school’s spare adrenaline devices.
- Understand the impact allergy can have on a child or young person’s wellbeing.
- Understand the school, college or setting’s allergy safety policy.
- Know how to check whether an individual is on the record of those with known allergy, and how to use an Allergy or Asthma Action Plan.
- Understand their responsibilities in reducing the risk of individuals with known allergy coming into contact with their known allergens.
- Understand how to report an allergic reaction or case of anaphylaxis, whether an incident or a near miss.
- Outcomes 9, 10 and 11 are specific to each school’s own systems. Whatever training you buy, someone in your school has to add the local layer: this is our policy, this is where our record is kept, this is where our spare kit lives.
Note also how much of the list sits outside conventional first aid content. Prevention, policy, wellbeing, record-keeping and reporting account for six of the fourteen. That is precisely why the guidance says first aid training is not sufficient, and why allergy awareness training should be understood as something that sits alongside first aid training rather than inside it.
Spare adrenaline devices: what has changed
There are now two types of licensed adrenaline device. As well as the familiar adrenaline auto-injector (AAI), a non-injectable nasal adrenaline device is now licensed. Clinical advice is that anyone at risk of anaphylaxis should carry two devices at all times, whatever the type, because two doses may be needed.
But only AAIs can be held as spares. Nasal adrenaline devices can be prescribed to an individual but cannot currently be stocked by a school as a spare. If a child prescribed nasal adrenaline has a reaction and their own device is not available, the school’s spare AAIs should be used. This is a genuinely important detail and one that will catch people out.
How many, and where. The guidance expects all schools to stock spare devices of the correct dosage for their pupils:
- one pair of 150 microgram devices for a state-funded nursery school;
- one pair of each dosage for primary and special schools;
- one or two pairs of 300 microgram devices for secondary schools.
- Secondary schools with large sites should consider two pairs, and schools operating across more than one site need appropriate dosages on each site.
The five-minute rule. You should give adrenaline within five minutes, which means you must be able to bring devices to the person within five minutes of anywhere someone might need them.
Store spares in pairs, label them clearly to distinguish them from prescribed devices, keep them accessible at all times, and never lock them away or keep them in an office with restricted access.
Many schools use a clearly marked emergency anaphylaxis kit containing the spare devices, the emergency asthma inhaler and spacer, and instructions. Please note: whereas you can give adrenaline autoinjectors to anyone you think is experiencing an anaphylactic reaction, whether or not they have a prescription for them; you can only give salbutamol inhalers for asthma if the person has a prescription for one.
Storage. Keep all adrenaline devices, prescribed and spare, at room temperature in line with manufacturer’s guidance. Do not refrigerate them, leave them in direct sunlight or put them anywhere that gets hot. The hot summer affected many adrenaline autoinjectors – always check the viewing window before giving an adrenaline autoinjector and ensure the liquid is clear and colourless.
Consent. The 2017 Regulations do not require consent for anyone to use a spare device in an emergency. It is good practice to obtain advance consent from parents so that you can assume consent, but in an emergency anyone may take reasonable action to save a life without stopping to check.
Note the contrast with emergency asthma inhalers, which you may only use for a child who already has a prescription for a reliever inhaler, and only where you have obtained written consent. These are two different legal positions that people easily confuse.
Recognising and treating a reaction
Mild to moderate allergic reaction: Signs include mildly swollen lips, face or eyes, mild throat tightness, an itchy or tingling mouth; hives or an itchy rash; abdominal pain or vomiting; or a sudden change in behav
iour, with no airway, breathing or circulation problems. If the child’s Individual Healthcare Plan says so, give an oral antihistamine. Phone the parent or emergency contact, and stay with the child at all times. They don’t usually need to go home or receive urgent medical attention, but keep them in a safe place and watch them closely for at least 60 minutes, because mild reactions can develop into anaphylaxis.
Antihistamines never treat anaphylaxis: Never let an antihistamine delay adrenaline. Antihistamines do nothing for the breathing and circulation problems that cause deaths. Since its 2021 update, the Resuscitation Council UK no longer recommends them as part of emergency anaphylaxis treatment. They may only help skin symptoms once the child is stable. If you see any airway, breathing or circulation problem, or have any doubt at all that it could be anaphylaxis, give adrenaline immediately.
Under-treating anaphylaxis is far more dangerous than over-treating a mild reaction.
Vomiting deserves particular attention. It appears in the DfE’s mild to moderate list, but Benedict’s mother told his inquest that vomiting was always the first symptom of his reactions. In a child with a known food allergy who has just eaten, sudden vomiting should make you think reaction rather than sickness bug, and a second episode is deterioration rather than reassurance. Where a child’s reactions characteristically begin with vomiting, ask their allergy clinician to write that into their Allergy Action Plan, so that no member of staff has to make the judgment.
Anaphylaxis can occur with no rash at all. Skin signs are absent in 10 to 20% of reactions, and that presentation is common in fatal cases. If a child known to have a food allergy suddenly develops difficulty breathing, always consider anaphylaxis. Giving adrenaline in that situation is very safe and may be lifesaving.
In an emergency:
- Place the child flat with their legs raised (unless they are struggling to breathe). If they are having difficulty breathing, position them into the lazy W position.
- Bring the adrenaline to them. Never take them to the adrenaline, and never let someone having anaphylaxis stand or walk around
- Give adrenaline as soon as possible, within five minutes. Do not wait to call the emergency services first
- Call 999 immediately and ask for an ambulance
- Use their own prescribed device first if it is available; if not, or if it misfires, use a spare
- Give a further dose after five minutes if there is no improvement
- Stay with them for at least one hour
- Never give a reliever inhaler instead of adrenaline. An Allergy Action Plan may direct a reliever dose after adrenaline if wheezing persists
Reactions to food usually begin within 30 minutes of eating the trigger, though they can occasionally occur four to six hours later. Once a reaction starts it progresses quickly: investigations into fatal anaphylaxis indicate a window of only 20 to 30 minutes in which action can prevent death.
Asthma or anaphylaxis?
Many food-allergic children also have asthma, and wheeze occurs in both. Fatal anaphylaxis in children is primarily a breathing problem, which means it is frequently mistaken for an asthma attack and treated with a reliever inhaler while adrenaline is delayed.
The order is settled across every authority. Adrenaline first, reliever afterwards if the plan calls for it, never the reliever instead. Treat breathing difficulty as anaphylaxis if the child has eaten or been stung recently, if there is any symptom outside the chest, if the throat or voice is involved, if the onset is sudden and out of their usual asthma pattern, or if the reliever is not working.
A child with both conditions should have an Allergy Action Plan and an Asthma Action Plan attached to their Individual Healthcare Plan. It is worth reading them side by side and asking the clinician to resolve any contradiction in advance, rather than leaving staff to work it out during an emergency.
Why training every member of staff matters
- Around one in five children and young people with allergy have their first everreaction at their school, college or early years setting
- Up to 20% of anaphylaxis reactions in schools happen in children with no pre-existing allergy diagnosis
- One in five anaphylaxis deaths among school-aged children in the UK happen in school
You cannot plan your way to safety using only the list of children you already know about. For a child having their first reaction there is no Individual Healthcare Plan, no Allergy Action Plan and no prescribed device. They will need help fast from whoever happens to be in the room, which is the strongest possible argument for training everyone rather than only designated first aiders.
Staff who act are protected
Hesitation costs lives, and much of it comes from fear of doing the wrong thing. The guidance addresses this head on, and every member of staff should hear it:
“If an individual (whether a child, young person, member or staff or visitor) experiences a life-threatening medical emergency, anyone – staff, volunteers or bystanders – may take reasonable action to save their life. The law recognises that rescuers act under extreme pressure. People who attempt to save a life in good faith are protected, even if an injury occurs while giving emergency care… Staff in schools, colleges and early years settings should be reassured that mistakes, hesitation, or imperfect technique do not amount to serious and wilful misconduct. The expectation is simply that staff act reasonably, to the best of their ability, in an emergency.”
Allergy and safeguarding
Allergy management sits within a school’s wider duty to safeguard and promote the welfare of its pupils. Preventing impairment of children’s health is part of safeguarding, as Working together to safeguard children makes clear.
But both the allergy guidance and Keeping children safe in education 2026, at paragraph 252, are careful about what that does and does not mean. An incident relating to the management of a child’s medical condition or allergy would not, in itself, warrant a safeguarding referral. Make a referral if an incident suggests the child’s condition puts them at increased risk of neglect, abuse or exploitation. This could happen, for example, if parents or carers fail to pass relevant information about the allergy to the school, or repeatedly send the child in without essential medication.
The distinction matters. It protects families from being referred over an honest school error, while making clear that a pattern of a child arriving without their adrenaline is a welfare concern that needs acting on.
“Nut aware”, not “nut free”
The guidance discourages nut-free policies. They create a false sense of security: nuts are one of fourteen key allergens, any food can cause a reaction, and precautionary labelling such as “may contain nuts” makes a genuine nut-free environment nearly impossible to deliver.
>The DfE recommends an allergy aware or nut aware environment instead — actively identifying risks, taking reasonable steps to minimise exposure to known allergens, and having robust emergency plans. You may still wish to discourage particular foods, but awareness and preparedness matter more than a ban on the label.
Serious incidents and near misses
Record them. Report them to the child’s parents or carers as soon as possible, and to the governing body. For a young person over sixteen, check first that they agree their parents should be told.
Share the report with the named leader for allergy safety, review whether the arrangements worked, and change the policy or the Individual Healthcare Plan if they did not. Where relevant, external reporting also applies: allergen-related food safety incidents to the local authority, incidents resulting in death or immediate hospitalisation to the HSE under RIDDOR, and notification to the relevant clinician where a care plan was involved.
Note too that the effect of exposure may be delayed and only recognised once a child is home. So reporting cannot rely on staff alone. Parents, the child and healthcare professionals may all need a route to report an incident to the school.
>The guidance puts the reason bluntly: failure to learn lessons from serious incidents and near misses has contributed directly to the deaths of children and young people in schools. That was one of the findings in Benedict’s case.
What good looks like beyond the clinical
The guidance also sets out examples of practice that is not acceptable, and they are worth reading as a self-audit. They include:
-
-
- Preventing children from easily accessing their own medication.
- Assuming a child does not have an allergy because they do not yet have a diagnosis.
- Sending a child who becomes unwell to the office or medical room without suitable supervision. In an allergic emergency, help must come to the child.
- Penalising allergy-related absence, including excluding children from 100% attendance rewards where absence is due to a medical condition.
- Requiring or pressuring parents to come in to administer medication.
-
Creating barriers to participation, including requiring a parent to accompany a child on a trip.
The guidance also asks schools to address allergy-related bullying, which can range from deliberately using known allergens to exclude a peer, through mockery of the need to avoid allergens, to threats to force-feed. Children with allergies are often already anxious and already feel singled out by the arrangements that keep them safe.
What schools need to do now
- Write and publish a dedicated allergy safety policy, using the DfE template as a starting point
- Name a senior leader responsible for allergy safety, and put allergy on the risk register
- Book whole-staff allergy awareness training against the fourteen outcomes above, and plan how to cover new, supply and cover staff (Link to our Anaphylaxis course)
- Audit your spare adrenaline stock: correct dosages, in date, in pairs, clearly labelled, accessible, and within five minutes of everywhere
- Time the retrieval route from the furthest point on site, at your slowest pace – ensure you can get to the adrenaline autoinjectors within 5 minutes.
- Check every child at risk of anaphylaxis has an up-to-date Individual Healthcare Plan and both prescribed devices with them
- Check whether any child is prescribed a nasal adrenaline device, and make sure staff understand that your spare AAIs would be used if it is unavailable
- Check that children with both asthma and allergy have plans that agree with each other
- Put an incident and near-miss recording process in place, with a route for parents to report
- Review your attendance, trips and behaviour policies against the unacceptable practice list
Key Sources
- Benedict’s Law, Benedict Blythe Foundation
- Judiciary UK – Prevention of Future Deaths Report
- Mishcon de Reya – Allergen Management in Schools: Lessons from the Benedict Blythe Tragedy
How we can help your school prepare
Standardising this practice across the UK is a huge step forward. If your school needs support meeting these new requirements, First Aid for Life is here to help.
Book our First Aid for Anaphylaxis and Acute Allergic Reaction online course or email emma@firstaidforlife.org.uk to arrange practical training to ensure your staff are fully trained, confident, and prepared for September 2026.
Online First Aid Course
The easiest way to learn these life-saving skills
Anaphylaxis and Acute Allergic Reaction Course ?
Learn at your own pace, stop and start as often as you like, and have full access for an entire year.
About us
First Aid for Life provide award-winning first aid training tailored to your needs. Please visit our site and learn more about our practical and online courses. It is vital to keep your skills current and refreshed. We are currently providing essential training for individuals and groups across the UK. In addition, we have a great range of online courses. These are ideal as refreshers for regulated qualifications. Or as Appointed Person qualifications. You can attend a fully regulated Practical or .online first aid course to understand what to do in a medical emergency. Visit firstaidforlife.org.uk or call 0208 675 4036 for more information about our courses.
First Aid for life provides this information for guidance and it is not in any way a substitute for medical advice. First Aid for Life is not responsible or liable for any diagnosis made, or actions taken on this information.



0 Comments